
Back pain lasting more than 12 weeks, returning repeatedly, worsening over time, or continuing despite appropriate treatment needs a clearer explanation than “the MRI shows degeneration.” By the end, you will know which warning signs need urgent care, when a spine neurosurgeon consultation is appropriate, what surgery can and cannot fix, and how to compare a specialist before deciding.
Key takeaways
- Seek reassessment when back pain lasts over 12 weeks or keeps worsening.
- Urgent review is needed for weakness, bladder changes, or loss of bowel control.
- Confirm whether pain comes from nerve compression, spinal instability, or another condition.
- Choose surgery only when the diagnosis and non-surgical options support it.
When Persistent Back Pain Needs More Than Self-Care
Back pain becomes persistent when it lasts more than 12 weeks, returns repeatedly, or follows a worsening pattern instead of settling. Pain that continues after an appropriate course of physiotherapy, activity modification, medication, or other pain management also deserves reassessment rather than indefinite self-care.
Stop relying on routine care and seek urgent assessment if you develop:
- New loss of bladder or bowel control
- Numbness around the inner thighs, buttocks, or genitals
- Progressive leg weakness or foot drop
- Fever with back pain
- Unexplained weight loss
- A history of cancer with new back pain
- Severe pain after a significant fall or other trauma
Without these warning signs, persistent pain does not automatically mean you need surgery. Arrange a spine neurosurgeon consultation when pain limits walking, work, sleep, or basic activities; leg pain, numbness, or weakness persists; or a routine orthopaedic review and structured rehabilitation have not produced a clear diagnosis or functional improvement.
The consultation should connect your symptoms, neurological examination, and actual MRI images—not just the radiology summary. Disc bulges, dehydration, and degeneration are common without pain, so an operation must target a convincing pain source and a meaningful functional problem. Take your previous reports and MRI images to the appointment.
Searches for the best neurosurgeon spine surgery for persistent back pain can mislead if they rely on ratings or advertising alone. Ask what diagnosis explains your symptoms, what non-surgical options remain, what surgery aims to improve, and the expected recovery, complications, and chance of persistent symptoms.
Finding the Cause: Nerve Compression, Instability, or a Non-Spinal Problem
Persistent back pain lasting more than 12 weeks can come from a compressed nerve, an unstable spinal segment, or a problem outside the spine. A spine neurosurgeon consultation should connect your pain pattern, neurological examination, functional limitation, and imaging before anyone recommends surgery.
| Possible source | Clues that support it | What the MRI or examination must show |
|---|---|---|
| Herniated lumbar disc | Leg pain below the buttock, tingling, numbness, or weakness in a matching nerve distribution | A disc fragment contacting the same nerve root |
| Spinal stenosis | Buttock or leg pain when standing or walking, relieved by sitting or bending forward | Narrowing around the symptomatic nerve roots |
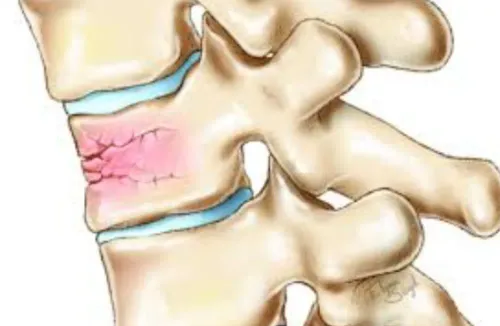
| Spondylolisthesis or instability | Back pain with movement, recurrent episodes, or worsening pain under load | Vertebral slippage or instability, sometimes confirmed with standing or flexion-extension radiographs |
| Facet, sacroiliac, or muscular pain | Local back or buttock pain without consistent neurological loss | No convincing nerve compression; examination matters more than MRI |
| Hip, kidney, infection, or tumour-related pain | Pain with systemic symptoms, hip restriction, urinary symptoms, or pain unrelated to spinal movement | The scan must not be used to force a spinal diagnosis |
Disc bulges, disc dehydration, and “degeneration” appear on MRI in people without pain. The surgeon checks whether the level, side, and type of compression match your symptoms, numbness, weakness, and walking difficulty. A mismatched abnormality is not a sufficient surgical target.
Seek urgent assessment for progressive leg weakness, foot drop, saddle numbness, new bladder or bowel loss of control, fever with back pain, unexplained weight loss, cancer history, or significant trauma. Take the actual MRI images and prior reports to the consultation.
The surgeon should explain the proposed outcome, possible persistent symptoms, recovery, complications, and alternatives such as continued rehabilitation or a second opinion.
When Non-Surgical Treatment Is Still the Better Choice
Pain lasting more than 12 weeks does not, by itself, justify an operation. Before considering surgery, you need evidence that a particular spinal problem is causing the pain and that a structured non-surgical plan has failed.
1. Stay active and follow exercise-based rehabilitation. A programme may include walking, trunk and hip strengthening, mobility work, and advice on lifting or sitting. Avoid routine traction, acupuncture, TENS, belts, or corsets for uncomplicated low-back pain.
2. Review medicines with a clinician. Discuss the risks of NSAIDs, including stomach bleeding, kidney damage, and cardiovascular effects, rather than taking them indefinitely. Use injections selectively; an epidural injection may reduce nerve-root pain but does not repair a disc or stabilise the spine.
3. Reassess pain, walking distance, leg strength, sleep, and work after an adequate trial. Request specialist review sooner if weakness progresses, foot drop develops, or bladder or bowel control changes.
4. Ask a back pain surgery specialist to compare continued rehabilitation with surgery when symptoms remain disabling. MRI findings must match the painful side, affected nerve, and examination—not merely show age-related changes.
Moving to an operation is most defensible when persistent sciatica from a disc herniation or spinal stenosis has not improved with appropriate treatment, imaging confirms nerve compression, and pain or loss of function remains substantial. Progressive weakness, significant instability, or compression threatening neurological function can justify earlier surgery.
Surgery targets nerve pain or mechanical instability; it is not a reliable cure for nonspecific axial back pain.
Which Operation Matches the Diagnosis?
The operation should match the structure causing nerve compression or instability, not the word “degeneration” on an MRI report. Microdiscectomy and decompression target pressure on a nerve; fusion addresses movement or structural failure between vertebrae.
| Option | What the surgeon does | Diagnosis it addresses |
|---|---|---|
| Microdiscectomy | Removes the herniated disc fragment pressing on a nerve root, usually through a small opening | Sciatica from a lumbar disc herniation, when leg pain and imaging match and non-surgical care has failed |
| Decompression | Removes bone, ligament, or disc material to create space around a compressed nerve | Lumbar spinal stenosis causing leg pain, numbness, or walking limitation |
| Laminectomy | Removes part or all of the lamina, the bony roof over the spinal canal; it is one form of decompression | Central or lateral-recess stenosis, sometimes caused by enlarged joints or thickened ligament |
| Spinal fusion | Joins two or more vertebrae so painful abnormal movement stops; screws, rods, and bone graft provide stability | Confirmed instability such as symptomatic spondylolisthesis, deformity, fracture, tumour, infection, or a selected painful motion segment |
A laminectomy does not automatically require fusion. Fusion enters the discussion when decompression would create instability or when instability already exists. It is not a routine operation for nonspecific low-back pain.
Ask which symptom the proposed procedure is intended to improve, what happens if you continue rehabilitation, and whether weakness or progressive neurological signs make delay unsafe. Surgery can relieve nerve-root pain without eliminating every source of back pain.
How to Choose a Spine Neurosurgeon in Pune
Do not choose a surgeon from advertising, online ratings, or one successful case. For spine surgery for persistent back pain in Pune, compare specialist registration, regular experience with the proposed operation, and whether the surgeon treats a clearly identified pain generator rather than the scan alone. Persistent back pain by itself does not justify surgery.
| Check | Ask | Why it matters |
|---|---|---|
| Specialist status | Is the surgeon registered for neurosurgical practice? | Confirms relevant training |
| Procedure experience | How regularly do you perform this operation? | Experience should match your diagnosis |
| Hospital support | Are MRI, intensive care, and emergency services available? | Complications need rapid treatment |
| Treatment policy | What non-surgical options remain? | Surgery is not always the best next step |
| Results and risk | What are the complication, reoperation, and persistent-symptom rates? | Prevents unrealistic expectations |
Bring the actual MRI images or disc, not only the radiology summary. Also take prior reports, prescriptions, injection or physiotherapy records, a symptom timeline, and a list of medical conditions and medicines.
- Mark where pain travels and whether you have numbness, weakness, or foot drop.
- Record what walking, sitting, sleeping, or work activities you cannot do.
- Ask what diagnosis links your symptoms, examination, and MRI.
- Ask what improvement surgery targets, how long recovery takes, and what happens if pain remains.
- Ask whether continued rehabilitation or a second opinion is reasonable.
A consultation with Dr Dilip Kiyawat should produce those specific answers, not simply a recommendation based on “degeneration” in an MRI report.
Related products
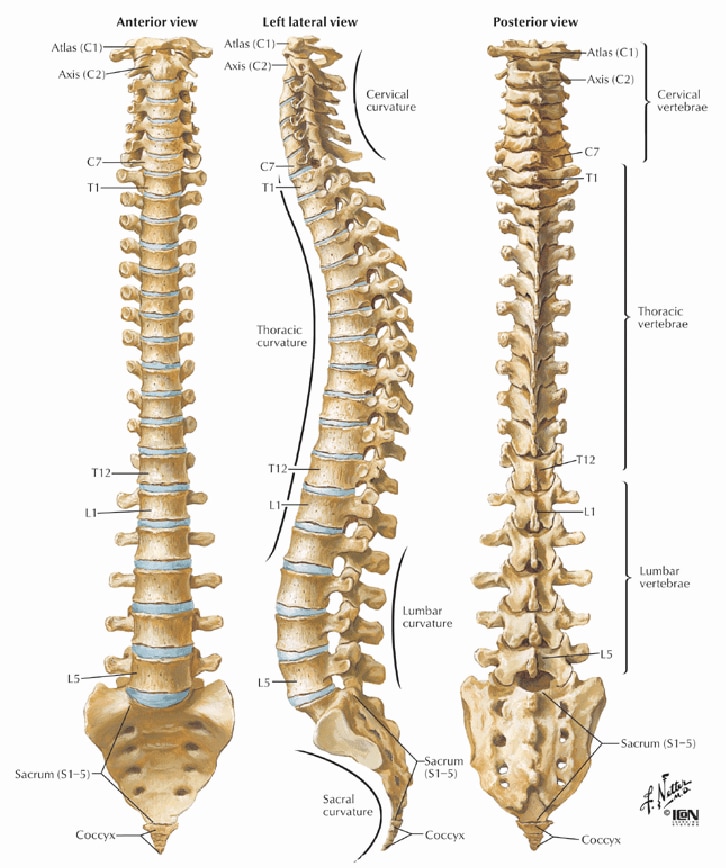 | Spine Surgery Spine Surgeon in Pune Dr. Dilip S. Kiyawat works as Neurosurgeon at Jehangir Hospital, Pune, Maharashtra, India. He completed his M.Ch.(Neuro). View product → |
 | Spine Surgery Prolapsed Lumbar Intervertebral Disc- Medical management The prolapsed lumbar intervertebral disc also referred to as slipped disc, sciatica, or just... View product → |
Frequently asked questions
When does persistent back pain need more than self-care?
Arrange a reassessment when pain lasts more than 12 weeks, returns repeatedly, worsens, or continues after physiotherapy, activity changes, medication, or pain management.
How can doctors identify the cause of persistent back pain?
A spine assessment distinguishes nerve compression, spinal instability, and non-spinal causes using your symptoms, examination findings, and appropriate imaging.
When is non-surgical treatment still the better choice?
Non-surgical care remains preferable when symptoms are manageable, no progressive neurological deficit exists, and the diagnosis does not support an operation.
Which operation matches the diagnosis?
The procedure depends on the problem: decompression addresses pressure on nerves, while stabilisation or fusion treats selected cases of spinal instability.
How should you choose a spine neurosurgeon in Pune?
Compare the surgeon’s experience with your diagnosis, explanation of treatment alternatives, expected recovery, risks, and follow-up care before choosing.
Related product
Brain Surgeon Here are numerous types of brain surgery. The type used is based on the area of the brain and the condition being treated. View product → |