A serious head injury can deteriorate before a family has time to compare specialists, so the first decision is emergency transport and rapid assessment—not booking a routine consultation. You will learn which warning signs demand immediate care, when surgery is justified, what hospital capabilities matter, and how to compare neurosurgical follow-up after the emergency has passed.
Key takeaways
- Call an ambulance for loss of consciousness, confusion, worsening headache, or new weakness.
- Do not move the neck or drive a deteriorating or unconscious patient.
- CT scans show bleeding, swelling, fractures, and pressure requiring urgent decisions.
- Choose a hospital with emergency CT, neurosurgery, intensive care, and operating-room access.
What should you do immediately after a serious head injury?
Call an ambulance immediately after a serious head injury if the person loses consciousness, becomes drowsy or confused, develops a worsening headache, or shows any new neurological change. Do not drive a deteriorating or unconscious patient: they may vomit, stop breathing, seize, or worsen without monitoring and airway support.
- Treat these signs as emergencies: repeated vomiting, a seizure, unequal pupils, weakness or numbness, slurred speech, difficulty speaking, poor balance, increasing drowsiness, or clear fluid or blood from the nose or ear.
- Keep the patient still and do not let them walk. Avoid lifting, twisting, or turning the head and neck; an unstable cervical-spine injury can worsen when the spine is moved.
- Support the head on both sides with towels or your hands without forcing the neck into position. Do not remove a helmet unless trained emergency staff need access to the airway.
- Monitor breathing, responsiveness, and vomiting while waiting. If the person is not breathing normally, follow the ambulance dispatcher’s instructions and begin resuscitation if told.
- Give no food, drink, alcohol, or medication unless emergency professionals instruct you. Record the injury time and any anticoagulant or antiplatelet drug, dose, and last dose.
“Best neurosurgeon brain surgery for after serious head injury” is an emergency-care question, not a routine search. Do not delay transport to arrange multiple opinions; trained emergency staff can stabilise the patient and route them to appropriate neurosurgical care.
How do doctors determine the type and severity of traumatic brain injury?
Doctors determine severity from the patient’s condition, examination, and imaging—not from one symptom alone. A head injury brain surgeon first ensures airway protection, keeps the cervical spine immobilised when injury is possible, and monitors oxygen saturation and blood pressure. The team reviews anticoagulants, antiplatelet medicines, sedatives, and alcohol use.
The initial neurological assessment records:
- Glasgow Coma Scale score for eye opening, verbal response, and movement
- Pupil size, equality, and reaction to light
- Limb strength, speech, sensation, confusion, and changes in alertness
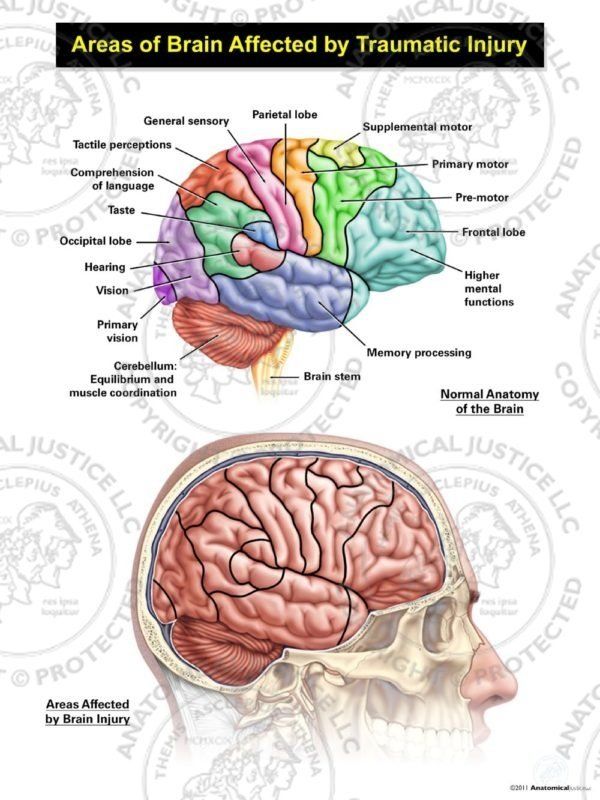
A non-contrast CT head scan is required for reduced consciousness, neurological signs, seizure, suspected skull fracture, significant loss of consciousness, worsening symptoms, or anticoagulant use. It can show an epidural haematoma, subdural haematoma, subarachnoid haemorrhage, cerebral contusion, depressed skull fracture, penetrating injury, compression, or midline shift.
| Finding | What it means | Consequence |
|---|---|---|
| Mass lesion | Blood or swollen brain occupies space | Compression can require urgent treatment |
| Diffuse axonal injury | Widespread shearing injury, often without a large clot | Severe impairment can occur despite a modest CT appearance |
| Normal first CT | No visible major bleeding or fracture at that time | Observation may still be necessary |
A normal scan does not end monitoring when anticoagulants or antiplatelet medicines increase bleeding risk, or when alertness, pupils, headache, vomiting, or strength changes. Repeat examinations and CT imaging can reveal delayed bleeding or evolving swelling.
When is brain surgery recommended, and when is observation safer?
Every serious head injury does not need brain surgery after head injury. A stable patient without dangerous compression may be safer with active observation and treatment:
- Close neurological checks and repeat CT scans
- Intensive-care monitoring
- Oxygen and blood-pressure control
- Seizure precautions
- Medical treatment to lower intracranial pressure
Observation is not “doing nothing”; it detects deterioration while avoiding an operation that offers no benefit.
Surgery becomes urgent when a clot, swelling, fracture, or neurological decline threatens the brain. Common triggers are:
- An epidural haematoma larger than 30 cm³
- An acute subdural haematoma thicker than 10 mm or causing more than 5 mm of midline shift, regardless of Glasgow Coma Scale score
- A deteriorating Glasgow Coma Scale score or abnormal pupils
- Persistent intracranial hypertension
- A large or expanding contusion, dangerous brain compression, an open or depressed fracture, or a penetrating injury
Intracranial pressure above 22 mm Hg is a commonly used treatment threshold. The decision also depends on pressure trends, cerebral perfusion, examination findings, age, other injuries, CT changes, and response to treatment; a cerebral perfusion pressure around 60–70 mm Hg is commonly targeted.
Decompressive craniectomy is reserved for selected severe cases when pressure remains uncontrolled despite medical treatment. It is not a default operation for every severe head injury.
What makes a neurosurgeon and hospital the right choice in an emergency?
The right emergency choice is the team that can assess, scan, operate, and provide neurocritical care without delay—not simply the most prominent “best neurosurgeon head injury” result online. The operation depends on the clot, fracture, swelling, neurological examination, and intracranial pressure.
| Option | What it means | When it applies |
|---|---|---|
| Craniotomy with clot evacuation | Opens the skull and removes an epidural or subdural clot | A mass lesion is compressing the brain |
| Decompressive craniectomy | Removes a skull section and leaves it off temporarily | Intracranial pressure remains dangerous despite treatment |
| Skull-fracture elevation and dural repair | Lifts a depressed fracture and repairs the protective membrane | Bone or torn dura threatens the brain |
| Intracranial-pressure monitoring | Measures pressure through a specialised probe or catheter | Severe injury requires continuous pressure-guided treatment |
Choose a hospital with:
- A 24-hour emergency department and immediate non-contrast CT
- Neurosurgical operating access, neuroanaesthesia, blood products, and intensive care
- Cervical-spine immobilisation, CT assessment, and combined brain-and-spine trauma management
- Coordinated trauma transfer, rehabilitation, discharge supervision, and follow-up imaging
Ask who personally reviews emergency referrals, whether a neurosurgeon is available at all hours, whether neurocritical-care staff manage raised pressure, and which centre receives the patient if transfer is required.
For non-immediate review in Pune or Pimpri-Chinchwad, Dr Dilip Kiyawat can help assess ongoing neurosurgical needs, but a deteriorating patient needs an ambulance and emergency hospital assessment, not a routine appointment.
Related items
 | Treatment of Head injury ₹1200 Management of head injuries 1. Extensive scalp laceration- . The bleeding is controlled by suturing the scalp. . View service → |
Brain Surgeon Here are numerous types of brain surgery. The type used is based on the area of the brain and the condition being treated. View product → |
What should recovery and follow-up include after neurosurgical treatment?
After discharge or hospital observation, recovery is safer when one clinician or team owns the plan. Confirm who supervises the patient, which symptoms require an emergency return, when repeat CT or other imaging is needed, and when the next neurosurgical review will occur.
- Arrange supervision for confusion, drowsiness, poor balance, or reduced independence. Return immediately for worsening headache, repeated vomiting, a seizure, new weakness, unequal pupils, worsening alertness, or speech difficulty.
- Take painkillers, antiseizure medicines, steroids, and blood thinners exactly as prescribed. Do not restart aspirin, warfarin, or similar medicines without explicit medical advice.
- Keep the imaging and discharge summaries. Ask whether a repeat CT is needed after surgery, a significant bleed, changing symptoms, or treatment with anticoagulants or antiplatelet drugs.
- Confirm follow-up with the neurosurgeon and the rehabilitation team, including wound review, staple or suture removal, activity limits, driving advice, and return-to-work planning.
Antiseizure treatment is not automatically lifelong. In severe traumatic brain injury, phenytoin can reduce seizures during the first seven days, but it does not prevent late seizures; longer treatment needs an individual reason, such as a seizure or specific cortical injury.
Persistent problems with memory, behaviour, balance, speech, swallowing, or limb strength require coordinated neurorehabilitation. Judge neurosurgical treatment after trauma by continuity from emergency care and pressure management through rehabilitation and review—not by a generic claim that a surgeon is “best.”
Frequently asked questions
What should you do immediately after a serious head injury?
Call an ambulance if the person loses consciousness, becomes drowsy or confused, develops a worsening headache, vomits repeatedly, has a seizure, or shows new weakness, numbness, speech trouble, or unequal pupils. Keep the person still, protect the neck, monitor breathing, and do not give food, drink, or medicines unless emergency clinicians advise it.
How do doctors determine the type and severity of traumatic brain injury?
Doctors assess consciousness with the Glasgow Coma Scale, examine pupils and limb strength, ask how the injury occurred, and perform an urgent CT scan when indicated. CT can show epidural or subdural haematoma, brain contusion, swelling, skull fracture, hydrocephalus, or midline shift. Repeat scans and MRI may be needed when symptoms change or the first scan does not explain them.
When is brain surgery recommended after a head injury?
Surgery is considered when bleeding compresses the brain, causes midline shift or herniation risk, raises intracranial pressure, or produces neurological deterioration. Procedures include opening the skull to remove a haematoma, evacuate contused tissue, control bleeding, or create space for swollen brain tissue. Small, stable injuries without dangerous pressure can be safer to monitor with examinations and repeat imaging.
What makes a neurosurgeon and hospital the right choice in an emergency?
Choose a hospital with 24-hour emergency CT, anaesthesia, neurosurgery, neurocritical care, blood-bank support, and an operating theatre. Ask who will review the scan, whether a neurosurgeon is immediately available, how repeat imaging will be arranged, and where the patient will receive airway and intracranial-pressure monitoring.
What should recovery and follow-up include after neurosurgical treatment?
Follow-up should cover wound or drain care, repeat CT or MRI when ordered, seizure and blood-thinner instructions, headache and pain control, sleep, memory, mood, balance, speech, and limb strength. Arrange rehabilitation for physical, occupational, speech, or cognitive problems. Return urgently for worsening headache, repeated vomiting, increasing sleepiness, seizure, fever, wound discharge, or new neurological symptoms.